Neck pain is not automatically a spine emergency, but weakness, clumsy hands, walking changes, trauma or systemic illness changes the decision quickly. Use the symptom pattern, duration and response to self-care to decide whether you need home measures, a general physician, physiotherapy, an orthopaedic appointment or immediate hospital assessment.
Key takeaways
- Seek emergency assessment after trauma or worsening weakness, numbness, balance problems, or fever.
- Arm pain, tingling, or weakness can indicate nerve irritation from the neck.
- Arrange specialist review when pain persists despite sensible self-care or keeps returning.
- Scans are most useful when examination findings suggest nerve, spinal cord, or structural problems.
Which neck pain symptoms require immediate hospital assessment?
Do not wait for a routine appointment if neck pain follows a road accident or fall, or if you develop neurological or systemic warning signs. This is when neck pain needs specialist care in Pimpri Chinchwad: seek immediate hospital assessment, especially if symptoms are progressing.
- Marked tenderness directly over the middle of the neck after trauma
- New weakness in an arm, hand or leg, or worsening numbness
- Loss of hand coordination, trouble walking, imbalance or falls
- Numbness affecting both arms or both legs
- Loss of bladder or bowel control
- Fever with severe neck stiffness
- Severe, unremitting night pain, unexplained weight loss or a history of cancer
- Immunosuppression or intravenous drug use alongside new neck pain
These features can point to a cervical fracture, infection, tumour or spinal-cord compression rather than a muscle strain. Do not drive yourself if weakness, walking difficulty or loss of bladder or bowel control is present.
| Warning pattern | Possible concern | What to do |
|---|---|---|
| Neck pain after trauma with midline tenderness | Fracture or instability | Go to a hospital urgently; keep your neck still |
| Weakness, worsening numbness, clumsy hands or gait trouble | Spinal-cord compression | Seek emergency neurological and orthopaedic assessment |
| Fever, severe stiffness, weight loss, cancer history, immunosuppression or intravenous drug use | Infection or tumour | Obtain same-day hospital evaluation |
| Loss of bladder or bowel control | Severe cord involvement | Treat as an emergency immediately |
What do the pain pattern and hand or leg symptoms suggest?
A dull ache or stiffness that stays in the neck or upper shoulders, worsens with posture or movement, and eases with rest sounds more like muscle strain or mechanical pain. Cervical spondylosis and a cervical disc prolapse can produce the same pattern, so symptoms alone cannot confirm the exact cause.
A neck pain orthopedic doctor looks for a nerve or spinal-cord pattern:
- Burning or electric pain travelling from the neck into one arm, pins and needles in particular fingers, reduced grip, or an altered reflex suggests cervical radiculopathy from nerve-root compression.
- Clumsy hands, dropping objects, difficulty fastening buttons, imbalance, falls, or stiff legs suggest cervical myelopathy from spinal-cord compression. Arrange prompt specialist review rather than treating these as ordinary posture pain.
- Pain limited to the neck and shoulder without numbness, weakness, coordination change, or walking trouble is more consistent with mechanical pain, although examination is still needed if it persists or limits you.
An abnormal X-ray or MRI does not prove that a disc or cervical spondylosis is causing your pain. Disc bulges, narrowing, and age-related degeneration are common findings; the scan must match your pain distribution, strength, sensation, reflexes, and gait. MRI is useful when nerve-root or cord compression is suspected, but it cannot replace that examination.
How long should you try self-care before seeking a higher level of care?
If neck pain is mild and has no red flags, try structured self-care for several days rather than going straight to a specialist. Use relative activity modification: keep walking and working within comfort, avoid the position or movement that aggravates pain, and follow suitable prescribed exercises or symptom relief.
- During the first several days, remain active and avoid prolonged bed rest, heavy lifting and sustained screen or phone positions. Gentle, targeted exercise is preferable to complete rest.
- Arrange a general physician or physiotherapy review if the pain is not improving, continues towards two to four weeks, or repeatedly returns. The clinician can check movement, strength and sensation, then adjust your persistent neck pain treatment.
- Book an orthopaedic or other specialist assessment if pain remains disabling, fails a reasonable exercise-based plan, or spreads into an arm. Do not wait for routine physiotherapy if you develop arm or hand weakness, worsening numbness, altered sensation or loss of coordination.
Medication review matters before using anti-inflammatory tablets or other pain medicines. Tell the clinician if you have a stomach ulcer, kidney disease, take blood thinners, have liver disease, or have had a reaction to these medicines. New weakness, rapidly worsening numbness or walking difficulty requires prompt assessment rather than another round of home care.
What happens during neck pain diagnosis, and when are scans useful?
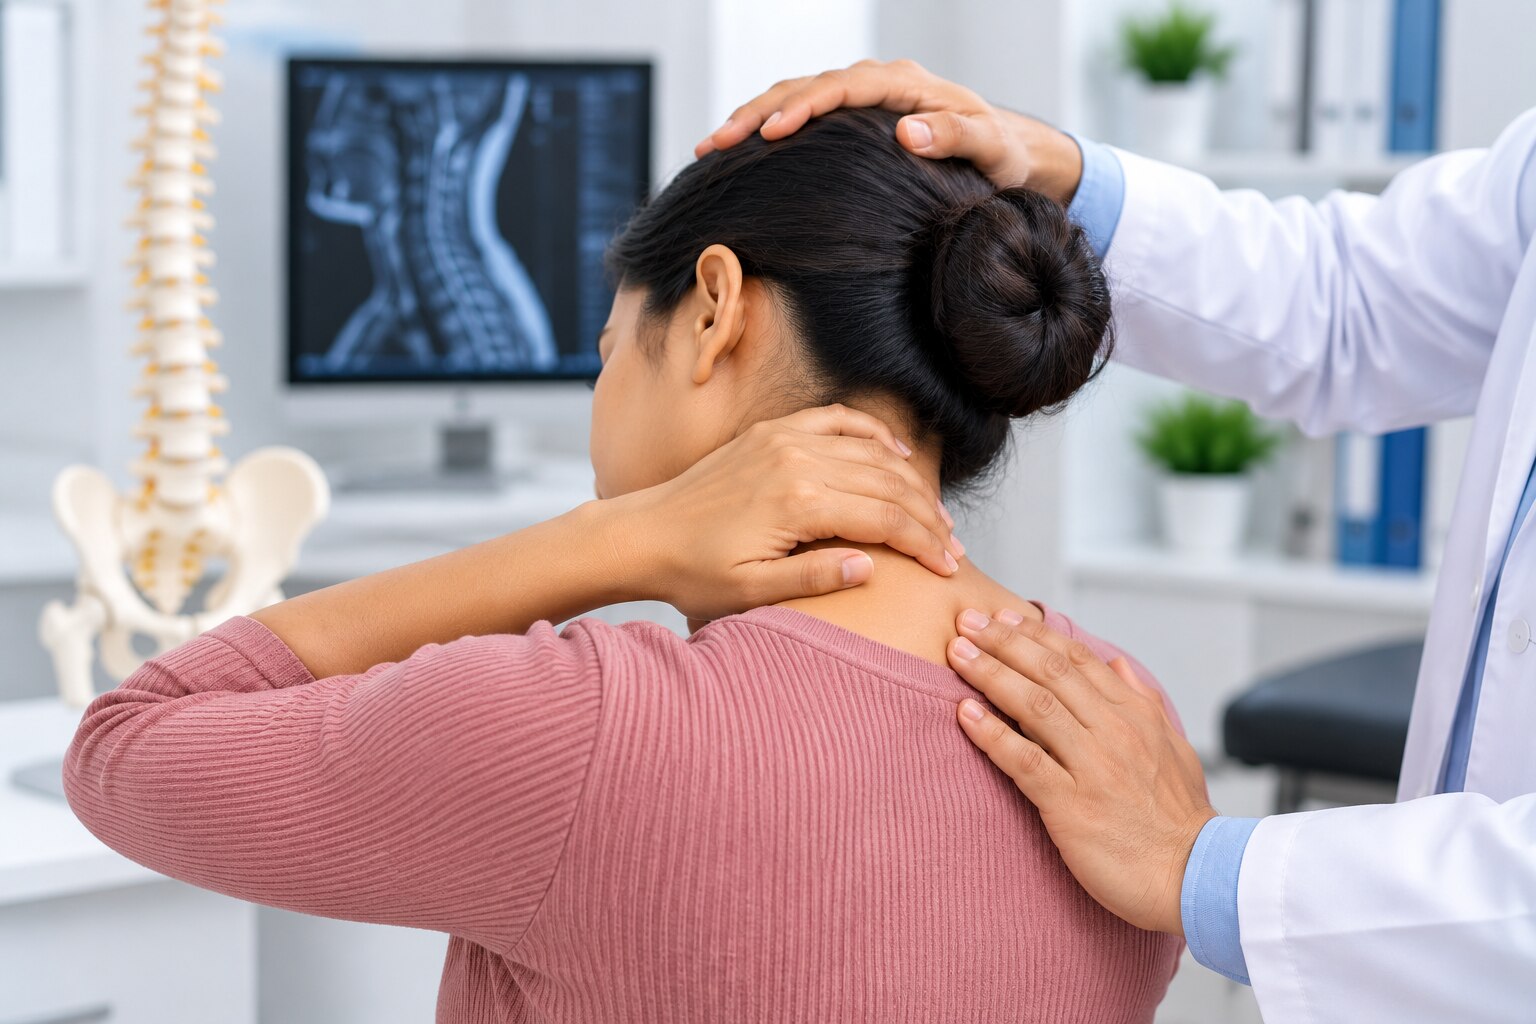
A proper neck pain diagnosis begins with history and examination, not an automatic scan. The clinician asks about injury, pain duration, radiation into the shoulder or arm, night pain, fever, cancer history and functional changes such as dropping objects or difficulty walking.
1. The examination checks neck movement, arm and leg strength, sensation, reflexes, gait and hand dexterity. It also looks for signs of cervical spinal-cord involvement, including clumsy hands, imbalance, stiff legs or worsening weakness.
2. The clinician then matches these findings to the pain pattern. Burning pain down one arm, finger tingling or altered reflexes can indicate nerve-root compression; weakness, gait change or loss of coordination needs prompt specialist assessment.
3. The clinician decides whether imaging will change treatment. Uncomplicated neck pain without trauma, neurological symptoms or red flags does not automatically require a scan.
Plain cervical X-rays suit selected initial situations, particularly acute or increasing pain without trauma, radiculopathy or warning signs. They show alignment, fractures and bony degeneration, but not nerves or discs clearly.
MRI is more useful when examination suggests nerve-root or spinal-cord compression, infection or tumour because it shows discs, nerves, the cord and soft tissues. CT defines many fractures better after trauma.
A report mentioning degeneration, narrowing or a slipped disc is not a diagnosis by itself. The finding must match your symptoms and examination; otherwise it may be incidental and treatment based on it can miss the real cause.
What should you expect from a neck pain specialist before surgery?
A useful appointment gives you a working diagnosis, not just a scan report. A neck pain specialist in Pimpri Chinchwad should examine strength, sensation, reflexes, gait and hand coordination, then classify the pattern as axial, radicular or myelopathic.
| Pattern | What it suggests | What the plan should address |
|---|---|---|
| Axial | Pain centred in the neck | Medicines, targeted exercises, physiotherapy and aggravating activities |
| Radicular | Nerve-root pain, numbness or weakness travelling into an arm | Examination-led imaging review and non-surgical care, with escalation if disabling symptoms persist |
| Myelopathic | Cord-related clumsiness, imbalance, stiff legs or widespread neurological change | Prompt specialist escalation and assessment for cord compression |
Ask how your medicines fit ulcers, kidney disease, blood thinners and other risks. You should leave with specific exercises, activity changes and a follow-up date, including the point at which worsening weakness, numbness or function requires earlier review.
Arm pain alone or an MRI showing a slipped disc, spondylosis or narrowing does not automatically justify surgery. Progressive neurological loss, significant cord compression, an unstable fracture, serious infection or tumour require urgent escalation; persistent disabling radicular pain despite non-surgical care can lead to discussion of decompression, fusion or disc replacement.
Avoid high-velocity neck manipulation until fracture, instability and cord compression have been excluded. Anand Orthopaedic Hospital may suit you when you need examination-led orthopaedic care, imaging review and a follow-up plan rather than a routine scan or operation package.
Related products
Spine problem & slip disc treatment. Spine problem & slip disc treatment. Dr Niranjan Ganjewar is well qualified to offer surgical treatment for the whole spine extending from the neck to the lower lumbar spine which... View product → |
Neck pain,backache treatment. Eight out of 10 people will suffer from back or neck pain at some point in their life. View product → |
Frequently asked questions
Which neck pain symptoms require immediate hospital assessment?
Seek immediate assessment after a road accident or fall, or when neck pain comes with worsening arm or leg weakness, numbness, trouble walking, loss of bladder or bowel control, severe headache, fever, or unexplained weight loss.
What do the pain pattern and hand or leg symptoms suggest?
Pain limited to the neck often points to a muscle, joint, or posture-related problem. Pain radiating into an arm with tingling or weakness suggests nerve irritation. Leg weakness, balance problems, or symptoms on both sides require urgent evaluation for spinal cord involvement.
How long should you try self-care before seeking a higher level of care?
Use gentle movement, activity modification, heat or cold, and suitable over-the-counter medicine as directed. Arrange specialist care if symptoms worsen, interfere with daily activities, recur frequently, or fail to improve after several days to a few weeks.
What happens during neck pain diagnosis, and when are scans useful?
A clinician reviews the onset, injury history, pain distribution, numbness, weakness, and medical conditions, then checks neck movement, reflexes, strength, sensation, and walking. X-rays, MRI, or CT are selected when examination findings, trauma, persistent symptoms, or red flags justify imaging.
What should you expect from a neck pain specialist before surgery?
A specialist should explain the likely pain source, examination findings, treatment choices, expected recovery, and warning signs. Non-surgical care often comes first unless spinal cord compression, progressive neurological loss, instability, or another urgent condition requires surgery.
Keywords